
Healthcare lead generation: reach the organizations that actually buy
Run healthcare lead generation by segment: list hospitals, clinics and labs by code, map who champions and signs, act on the triggers that open budgets.


Healthcare lead generation: selling to providers, not finding patients
Healthcare lead generation, in B2B, means finding the hospitals, clinics, laboratories and care facilities that could buy what you sell, identifying who champions, validates and signs the purchase inside each one, and opening a conversation at the moment a budget moves. The same phrase is also used for the opposite job, bringing new patients to a practice. That is patient acquisition, a consumer marketing problem, and it is not what this guide covers.
A 600-bed hospital and a four-doctor practice do not buy the same way, and treating them as one market is the first mistake most teams make. The people who use your product are rarely the people who sign for it: a nurse manager can champion a purchase that finance or IT then stops. And most deals start from an event inside the organization, such as a new unit, a merger or a software change. Build around those facts first. Channels come after. That is also the difference with regular B2B lead generation: a committee instead of a single buyer, a cycle counted in months for hospitals, and compliance questions that arrive before the contract.
| Question | Patient acquisition | B2B healthcare lead generation |
|---|---|---|
| Who is the lead? | A person looking for care | An organization and the several people who decide inside it |
| What triggers the purchase? | A symptom, a referral, a location | A new site, a merger, a hiring wave, a system change |
| How long does it take? | Days | Weeks for a small practice, often many months for a hospital |
| What do you measure? | Booked appointments | Accounts engaged, evaluations started, contracts |
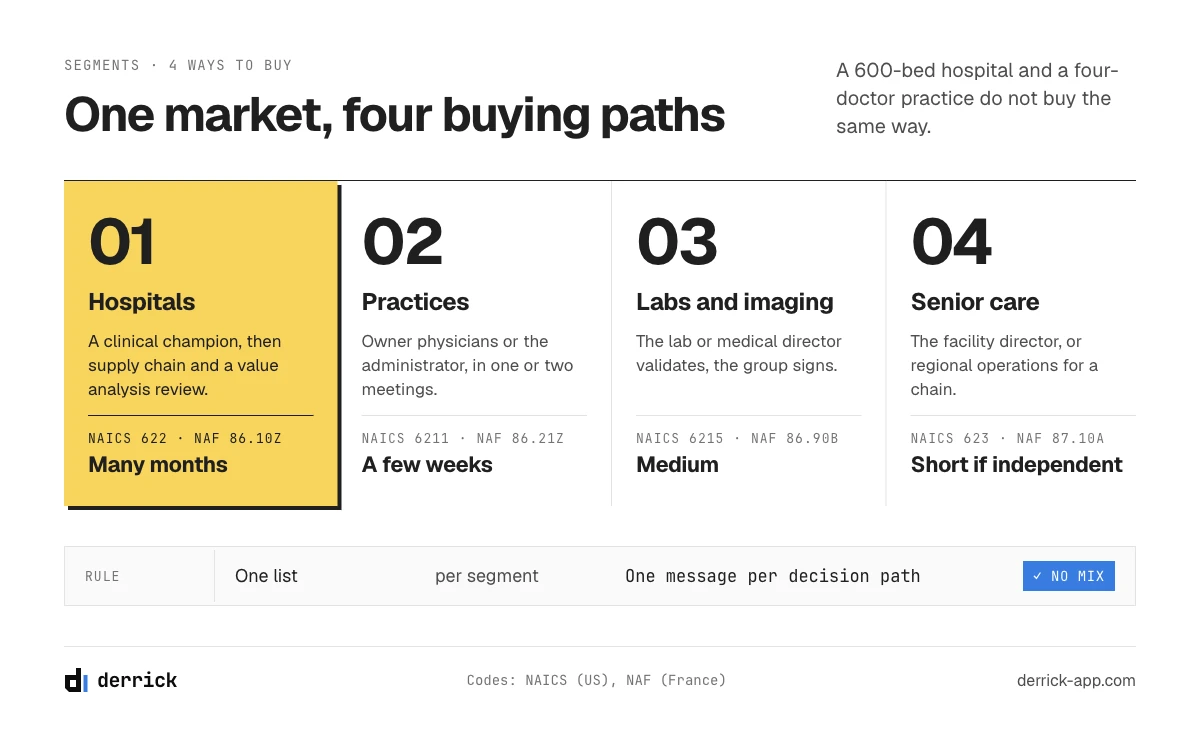
Four healthcare segments that buy in four different ways
Most healthcare lead generation fails at the first step, because "healthcare" is treated as one list. It is at least four, and each one has its own decision path and its own pace. The industry codes below are the ones data sources understand: NAICS in the United States and Canada, NAF in France.
| Segment | NAICS (US) | NAF (France) | How the decision is made | Typical cycle |
|---|---|---|---|---|
| Hospitals and health systems | 622 (622110 general hospitals) | 86.10Z | Clinical champion, then supply chain and a value analysis review; many purchases run through group purchasing contracts or tenders | Long, often many months |
| Physician practices and clinic groups | 6211, 6214 | 86.21Z, 86.22A to C | Owner physicians or the practice administrator, often in one or two meetings | Short, often a few weeks |
| Laboratories and imaging centers | 6215 (621511, 621512) | 86.90B, 86.22A | Lab or medical director validates, operations or the group signs | Medium, longer when the group buys centrally |
| Senior and long-term care | 623 (623110, 623312) | 87.10A | Facility director for independents, regional operations for chains | Short for independents, longer for chains |
Payers such as health plans, pharma, biotech and life sciences companies, and medical supply distributors also buy from B2B vendors, but through procurement and market access teams that work much like any large corporate account. This guide stays on the providers of care, because that is where medical lead generation differs most from the rest of B2B.
Two more filters matter as much as the segment. Independent or part of a group: a hospital inside a health system, or a clinic owned by a larger network, often loses purchasing power to the center. Selling to the site then means getting on a list decided elsewhere. Size of the site: bed count for hospitals and care facilities, number of physicians for practices, number of collection points or machines for labs and imaging. Size tells you how many people will be involved and how long the decision will take. Write these filters down as your ideal customer profile before you pull a single name.
Building the healthcare sales leads list: hospitals, practices, labs, care
Hospitals are public and well known. Practices, labs and small care operators are numerous and local, and many have a thin web presence. The list you need depends on the segment.
- Hospitals and health systems. The universe is small and public. The work is mapping the structure: which hospitals belong to which system, and where purchasing is decided. Start from your best customers and look for organizations like them.
- Practices and clinic groups. The universe is large and local. Industry codes and map search are the reliable sources, because many practices have no company page worth the name.
- Labs and imaging. Heavily consolidated in many countries. Find the groups first, then list their sites.
- Senior care. A mix of chains and independents. The chains are easy to find; the independents come from registries and maps.
Hospital sales leads
Hospital sales leads start with the structure, not with a name. First decide whether you sell to the system or to the site: a health system that runs several hospitals often signs supplier contracts once, at the center, while each hospital keeps its own clinical champions. Then record the bed count of each site, because it predicts how many departments and reviews a purchase will cross. Finally, note where purchasing is decided for your category: at the site, at the system, or through a group purchasing contract. A short list of hospitals mapped this way is worth more than a long file of names with no structure. If you run an account-based approach for health systems, treat the system as the account and each hospital as a sub-account with its own champion.
Filter the list before the first email
Two checks save a campaign. First, filter on what each organization says about itself on its own website. A practice that advertises concierge medicine or direct primary care runs on a different business model from one built around Medicare patients, and it buys differently: keep the first kind if that is where you win, set the second aside. Second, count the segment before you write a sequence. When a narrow segment holds only a few dozen organizations in your territory, every careless email burns an account you cannot replace, and calls, events and referrals deserve a bigger share of the effort than cold email.
Derrick builds each of these lists in its web app, or from a Google Sheet through the sidebar. One feature per source:
- Find Similar Companies takes one customer's LinkedIn company page and returns lookalike organizations with industry, country, website, LinkedIn URL and a similarity score. 1 credit per company, on the free plan, no account to connect.
- Import Companies from a Prompt takes a plain description such as "multi-site physical therapy clinic groups in Texas" and returns name, industry, country, website and LinkedIn URL. 1 credit per company with your LinkedIn account connected, 10 credits without.
- Import Companies by NAF Code pulls every French company registered under a code such as 86.90B straight from the SIRENE registry, with headcount and address. 1 credit per company, on the free plan.
- The Google Maps Scraper lists physical sites, practices and imaging centers included. 1 credit per place, on the paid plans.
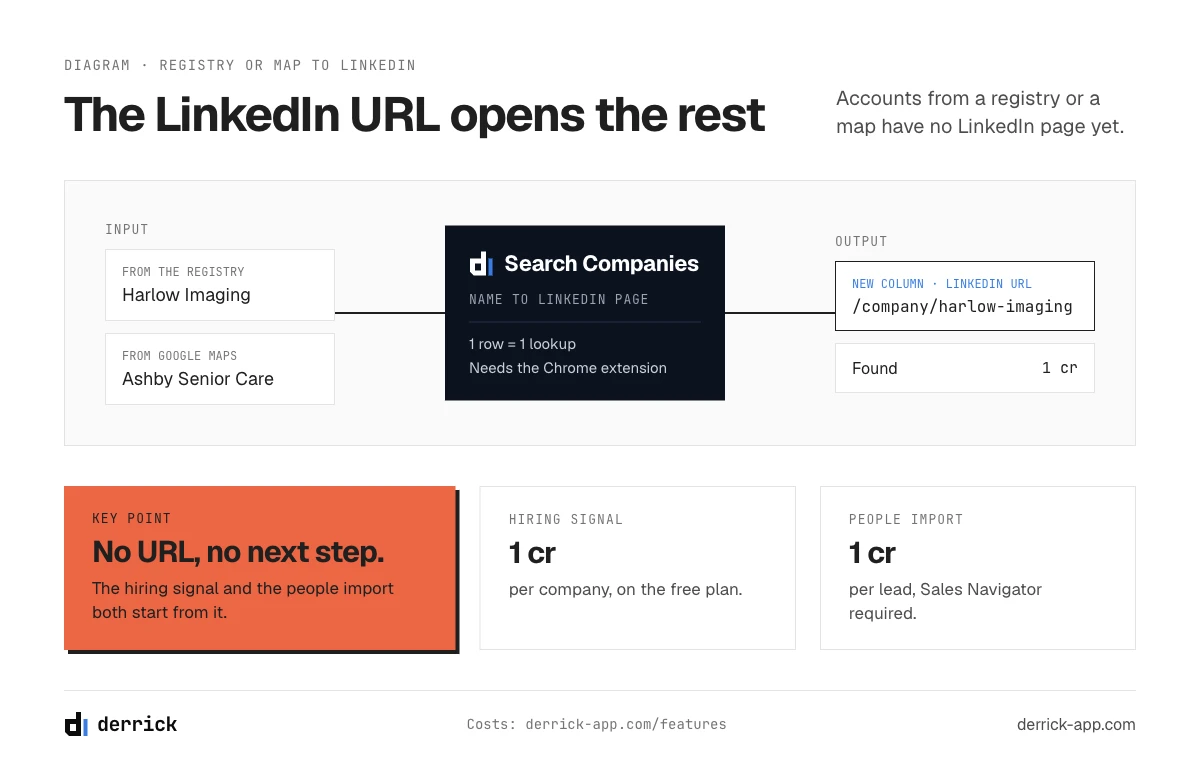
- Search Companies finds the LinkedIn page of an organization from its name, for accounts that came from the registry or from maps. 1 credit per company, with your LinkedIn account connected through the Derrick Chrome extension.
The LinkedIn URL matters because the next two steps, the hiring signal and the people import, both take the LinkedIn company page as input.
Who champions, validates and signs a healthcare purchase
A healthcare purchase usually involves a clinical or operational champion who wants the product, a validator who can block it, and an administrator who signs. In a hospital, those are different people in different departments, and a value analysis review may sit between the champion and the budget. In a small practice, the same physician can play all three roles. The combination depends on what you sell and to whom. Pick yours below.
Who decides inside the organization you are targeting?
Two questions. The answer shows the champion, the validator, the signer, the codes to pull the list with, and what the list costs in credits, from 100 accounts to a national list.
Which organizations are you targeting?
What do you sell them?
Answer the two questions to see the buying path.
Job titles vary from one organization to the next. Search on the function (nursing, IT, operations, facilities), not on one exact title.
The same map, in a table. The validator depends mostly on what you sell: biomedical engineering, pharmacy or value analysis for clinical products, IT security for software, HR and compliance for staffing, infection control for facilities work.
| Segment | Champion (devices or supplies) | Champion (software or IT) | Signs | Committee and validators |
|---|---|---|---|---|
| Hospitals and health systems | Head of the clinical department, with nursing leadership | CIO, or the head of the department that will use it | CFO, COO or head of supply chain | Value analysis committee, CMO or CNO, IT security, supply chain and procurement; credentialing and compliance for staffing |
| Practices and clinic groups | The physician partner who will use it | Practice administrator | Managing partner or practice administrator | Rarely anyone beyond the partners; the practice's outside IT provider for software |
| Labs and imaging centers | Laboratory or medical director | Lab information manager | Operations director or group purchasing | Quality manager, IT for connected instruments, group procurement |
| Senior and long-term care | Director of nursing | Facility director | Facility director, or regional operations for a chain | Director of nursing, regional operations, compliance for staffing |
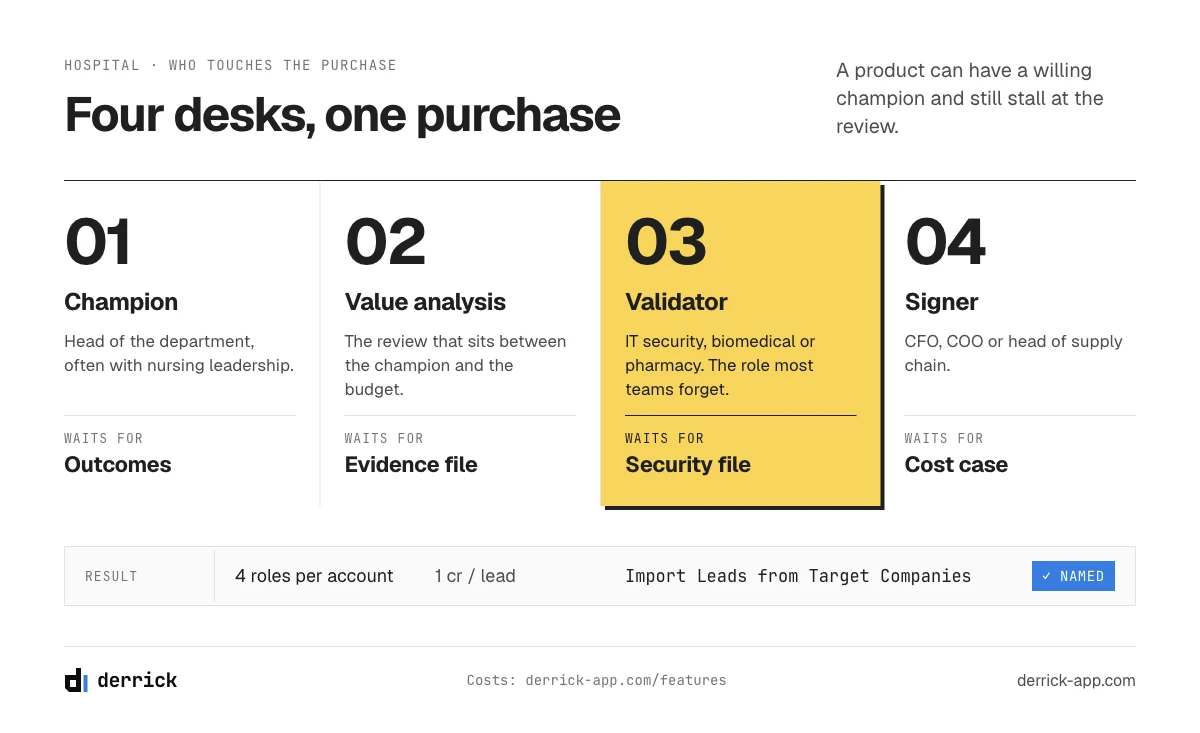
The validator is the role most sales teams forget. In a hospital, a product can have an enthusiastic clinical champion and still stall for months because nobody prepared the evidence file for the value analysis review, or because IT security was contacted last. Reaching them early shortens the cycle more than any follow-up email.
Once the roles are known, Import Leads from Target Companies turns the account list into a people list. You give it the LinkedIn company URLs of your accounts and a Sales Navigator search describing the roles, and it imports the matching people at each organization, at 1 credit per lead. It runs on the free plan, but it needs a Sales Navigator subscription and your LinkedIn account connected through the Derrick Chrome extension.
Healthcare lead generation triggers: the events that open a budget
The triggers worth watching in healthcare are hiring, a new site or service line, a merger or affiliation, a software change, an upcoming accreditation or inspection, and a new leader. Healthcare organizations rarely change suppliers without a reason, because switching means retraining staff and revalidating procedures. The window opens when something changes, and most changes are public.
- Hiring. A hospital recruiting ten nurses for a new unit, a lab hiring a quality manager, a clinic group posting its first IT role: each tells you what is changing, and when. It is the most reliable public trigger because it is dated and tied to a function.
- New site or service line. An outpatient center, a new imaging suite, a new specialty. New space means new equipment and new software, bought in the same window.
- Merger, acquisition or affiliation. Consolidation forces systems and contracts to converge. It can close a door (the group standardizes on someone else) or open one (the new owner reviews everything).
- Software change. A move to a new patient record or billing system pulls in integration and training work around it.
- Accreditation or inspection coming up. A deadline creates urgency for anything that helps the organization pass.
- New leader. A new CFO, head of nursing or administrator reviews suppliers in the first months.
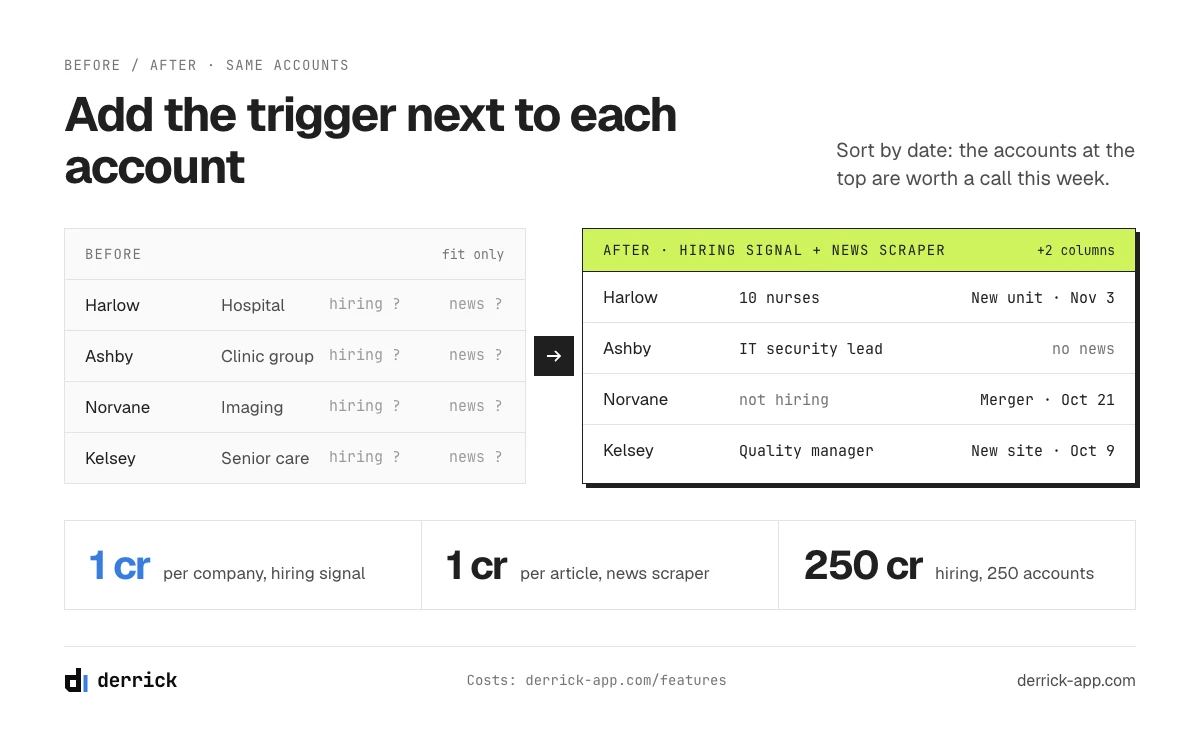
Two Derrick features turn these into a column in your list, in the web app or in your sheet. Company Hiring Signal reads the LinkedIn company URL of each account and shows whether it is hiring on LinkedIn, and for which roles, at 1 credit per company, on the free plan and without connecting an account. Google News Scraper returns the most relevant recent article for each organization, with title, publisher and date, at 1 credit per article on the paid plans. Sort by date, and the accounts at the top are the ones worth a call this week. The guide to selling to decision makers covers how to open with that trigger.
Healthcare lead scoring: fit plus trigger
Once the triggers sit next to the list, score each account on three things. Fit: the segment you win in, the size band, independent or part of a group. Trigger: a dated event in the last 90 days. Committee coverage: how many of the champion, validator and signer you have named. Set the weights from your own past deals, not from someone else's model. Scoring keeps healthcare lead generation on the accounts that can buy now. An illustration on three accounts, each criterion scored from 0 to 3:
| Account | Fit | Trigger | Coverage | Total and next step |
|---|---|---|---|---|
| Independent 300-bed hospital, posted IT security roles last month, CIO and value analysis lead named | 3 | 3 | 2 | 8 of 9: call this week |
| Clinic group of 12 sites in your best segment, no recent event, one contact | 3 | 0 | 1 | 4 of 9: check the triggers again next month |
| Health system with a merger in the news, nobody named yet | 2 | 2 | 0 | 4 of 9: map the committee before any outreach |
For US hospitals, add a public performance indicator. The Centers for Medicare & Medicaid Services publish patient experience scores (HCAHPS) for each hospital in the Patient survey (HCAHPS) dataset, the data behind Care Compare. Cross it with what Website Technologies sees on the hospital's website, such as online scheduling, a patient portal, a chat tool, the analytics and the CMS in place, at 2 credits per website on the paid plans. A hospital with weak patient experience scores and no online scheduling is a stronger fit for a patient engagement product than one that already runs both. Website Technologies reads the public website only: it does not see the patient record system or any clinical IT.
Compliance and group purchasing: HIPAA, GPOs and contracts
Two things sit between a willing champion and a signed order in US healthcare: the compliance question and the purchasing contract. Both are predictable, so prepare them before the first meeting.
HIPAA, in plain terms
HIPAA governs protected health information, meaning patient data. Prospecting a hospital's purchasing director with a business email is not patient data, so HIPAA does not decide who you can contact. It matters when your product will create, receive or store patient data. In that case the organization will expect a business associate agreement (BAA) before signing, and its IT security team will review how you handle the data. Say so in the first conversation, with your answer ready.
Automating outreach without touching patient data
Automating healthcare lead generation does not raise a HIPAA question as long as what you automate is business data: organization names, websites, job titles, professional emails. Keep patient information out of your prospecting tools entirely, notes and call summaries included, and never ask a prospect to share patient examples before a business associate agreement is in place. This is a working rule, not legal advice: your compliance team has the final word.
Group purchasing organizations
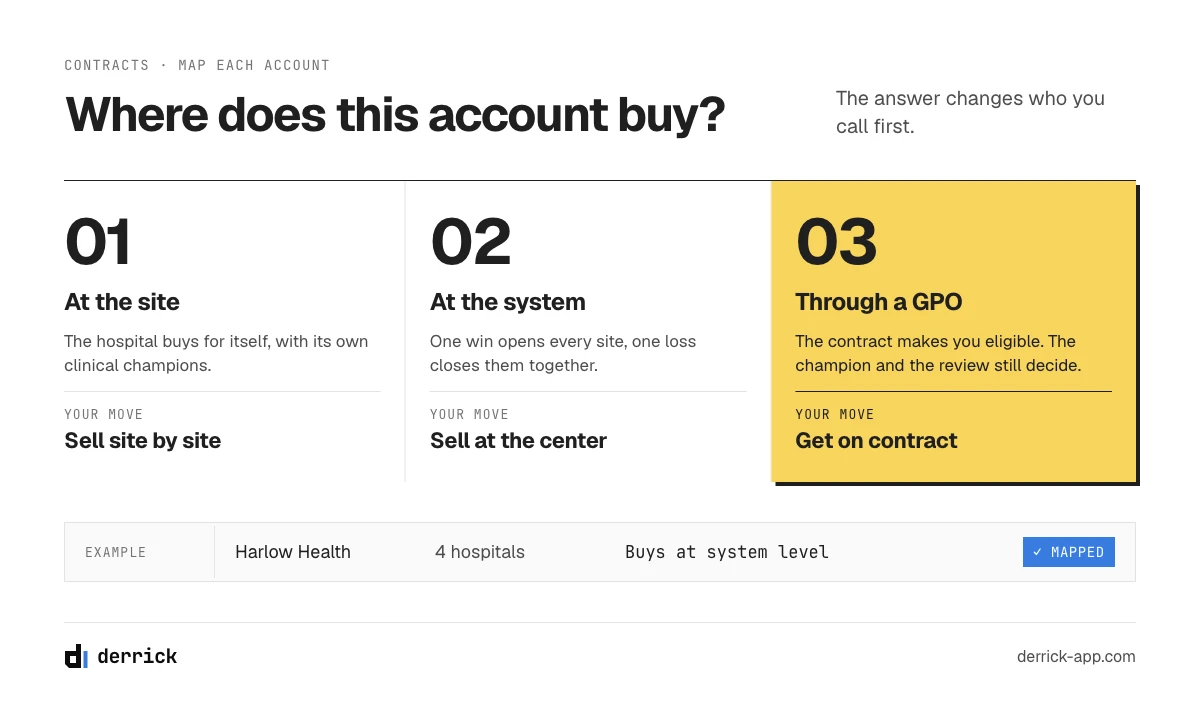
Many US hospitals buy a large part of their supplies through group purchasing organizations (GPOs). Vizient, Premier and HealthTrust are among the largest: they negotiate contracts on behalf of member hospitals, and members can then buy on those terms without running their own tender. For a supplier, being on contract with the right GPO can remove months from the cycle. It does not replace selling to each hospital, though. The contract makes you eligible; the champion and the value analysis review still decide whether you are used.
Health systems and central contracting
Integrated delivery networks often standardize suppliers across their hospitals and clinics. A win at system level opens every site at once, and a loss closes them together. Map where each account buys: at the site, at the system, or through a GPO contract. It changes who you call first.
Reaching clinicians and administrators without wasting their time
Clinicians spend their day with patients, not in their inbox. Administrators get vendor requests all week. Both respond to relevance and proof. Anything that smells like a mass campaign gets ignored.
Evidence first
Clinical and operational buyers want proof before a meeting: outcomes, time saved per shift, the effort to put it in place. A short case study from a comparable site does more than a brochure. Publish what a value analysis review will ask for, so your champion can forward it.
Content per role
In healthcare lead generation, each role waits for a different piece of proof. The clinical champion wants outcomes from a comparable site and what changes in the daily workflow. IT security wants the security file: where the data sits, who can access it, how you integrate. The signer wants the cost case: total cost over the contract, the savings, and what happens if the project stalls. Prepare all three before the first meeting, so the champion can forward each one to the right desk. Webinars work when a customer from the same segment presents with you, not as a product demo. Partnerships with a software vendor, a distributor or a consultant already working inside the account shorten the path to the committee.
Conferences and specialty associations
Each specialty has its own meetings and associations, and that is where clinical champions spend time with peers. Book meetings in advance with accounts from your list rather than waiting at the booth.
Trigger-based outbound, by role
Outbound works when each message is tied to a dated event and written for one role: the clinical benefit for the champion, the risk answer for the validator, the cost case for the signer. Send to two or three people per account in parallel. Email Finder finds professional emails at 5 credits per email found, on the paid plans. Phone Finder finds direct numbers at 200 credits per phone found, also on the paid plans, which makes it a tool for the few accounts where a call is clearly worth it. The same account-first logic drives lead generation for SaaS companies, many of which sell into healthcare.
When the buyer is the physician rather than the administration, building a verified physicians email list is its own method, with its own sources and checks, covered in a separate guide.
How many touchpoints does it take to convert? It depends on the segment and on how many roles you have to reach. A practice partner can answer after a couple of messages. A hospital needs two or three roles reached in parallel, each with the proof that fits the role, so count touchpoints per account rather than per person, and judge the program on the time from first meeting to contract.
Referrals and peer proof
Inside each specialty and region, healthcare is a small world. A reference call with a peer at a similar organization often unlocks a deal that five emails could not.
Where healthcare lead generation goes wrong
- Mixing segments in one campaign. A message written for a hospital supply chain team makes no sense to a practice owner.
- Selling to the user only. The clinician who loves your product does not sign. Give them what the validator and the signer need.
- Treating a health system as one account. Sites can have different needs while purchasing stays central. Map both levels.
- Ignoring who owns the site. A clinic that joined a larger group last year may no longer choose its own suppliers.
- Chasing patient-acquisition leads. People looking for care are not buyers of B2B products.
How to measure healthcare lead generation over a long cycle
With cycles that run from a few weeks to more than a year, counting leads per month tells you little. A download from a student counts the same as a download from a nursing director at a target hospital. Measure along the account path instead.
| Metric | What it tells you | How to read it |
|---|---|---|
| Committee coverage | Share of target accounts with a named champion, validator and signer | Below half, the list is the bottleneck, not the message |
| Trigger rate | Share of accounts with a dated trigger in the last 90 days | How many accounts are worth contacting now |
| Meetings per 100 accounts contacted | Targeting and message together | Compare by segment, never across segments |
| Evaluations started | Trials, demos to a committee, evidence files requested | The first strong sign of intent in healthcare |
| Time from first meeting to contract | The real length of your cycle, by segment | Plan pipeline coverage on it, not on a generic benchmark |
How long before the first meetings? It depends on the size of the list, the channel and the segment: practices and independent care facilities tend to answer within the first weeks of a well-targeted sequence, while hospitals answer when a trigger lines up with your message. Track meetings per 100 accounts contacted from the first week, and keep it apart from the time to contract, which is a different and longer clock.
Keep the account as the unit. Three contacts at one hospital is one opportunity, and your pipeline should show an explicit stage for the review step if you sell to hospitals.
Do it yourself or hire a healthcare lead generation company?
Most teams that look into healthcare sales lead generation end up comparing two options: build the program in house, or hire an agency that delivers lists, calls and booked meetings. Outsourcing makes sense when you have no SDR team yet, or when you need meetings quickly in one narrow segment to test a market. Building in house pays off when the cycle is long, when the committee has to be mapped account by account, and when your margin depends on keeping that knowledge. If you hire, judge the agency on six points:
- Real experience in medical lead generation, medtech included, with references in your segment
- Data quality and freshness, and how both are checked
- Qualified leads over volume, with a written definition of qualified
- Several channels, not email alone
- Coverage of your territories
- Who keeps the data and the account mapping when the contract ends
The general buy vs build lead generation comparison, with the pricing models agencies use, lives in a separate guide.
What a 250-account healthcare lead generation program costs in credits
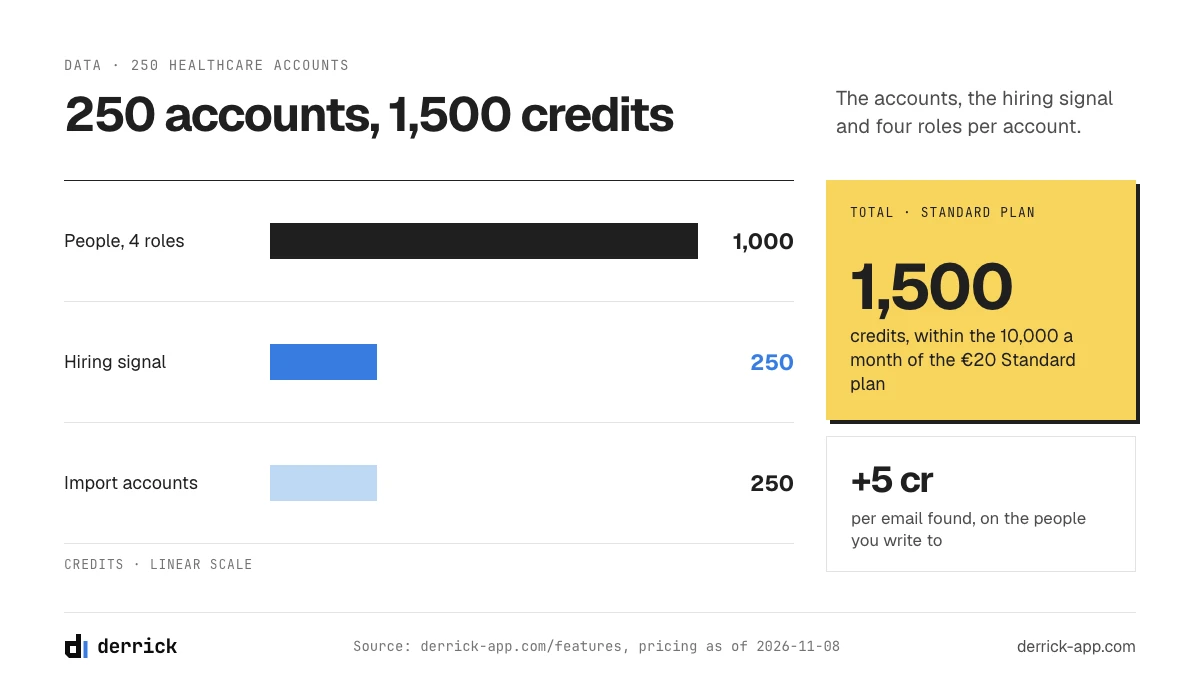
Here is the list, the committee and the triggers for 250 target organizations, done in Derrick, step by step.
| Step | Derrick feature | Unit | Volume | Credits |
|---|---|---|---|---|
| Import the accounts, with LinkedIn URL | Find Similar Companies, or Import Companies from a Prompt with LinkedIn connected | 1 per organization | 250 | 250 |
| Hiring signal | Company Hiring Signal | 1 per organization | 250 | 250 |
| People, four roles per account | Import Leads from Target Companies (Sales Navigator required) | 1 per lead | 1,000 | 1,000 |
| Total | 1,500, within the Standard plan (10,000 a month, 20 euros) |
Starting from the NAF registry in France instead? The import still costs 1 credit per company. Add 1 credit per company with Search Companies, with your LinkedIn account connected through the Chrome extension, to find its LinkedIn page before you run Company Hiring Signal and import the people. Email Finder on the people you decide to write to adds 5 credits per email found.
The same steps run on four surfaces. In the web app, with nothing to install. In Google Sheets, from the sidebar, where the list lives and the team works. From an AI assistant through the Derrick MCP server, in Claude, ChatGPT or any MCP client: "which of these clinic groups are hiring nurses this month?" And through the REST API, to enrich every new account in your CRM without anyone opening a sheet. The API and the MCP server come with the Plus plan and above, from 47.50 euros a month. The method works the same for 50 practices in one city or 5,000 sites across a country.
Start with the free plan and its 100 credits per month, or read the broader B2B lead generation guide first.
One email every 2 weeks with the new B2B marketing guides as we publish them and what we measure on prospecting and data quality. No spam, no resale. Sign up with the form in the middle of this guide, or from the homepage.
Frequently asked questions
What is healthcare lead generation?
Who makes purchasing decisions in a hospital?
How do I build a list of healthcare organizations to target?
What are the best triggers for healthcare sales outreach?
How long is the healthcare sales cycle?
Does HIPAA stop me from prospecting hospitals?
How much does it cost to build a healthcare prospect list with Derrick?
How do you generate leads for medical device companies?
Keep reading
Continue exploring this cluster


The State of B2B Marketing Performance 2026: Benchmarks Report
Read →
Account-Based Marketing (ABM): Definition, Techniques, Examples
Read →

Inbound vs Outbound Marketing: Differences, When to Pick Each
Read →

B2B Lead Generation: Strategies, Tools, Tips in 2026
Read →




